Tag: CMS (Medicare and Medicaid)

Goverment Shutdown: What you Need to Know
With the government shutdown in effect, the Texas Medical Association is in regular communication with federal colleagues at the American Medical Association on the impact to physician practices, as AMA remains in touch with senior officials at the Centers for Medicare & Medicaid Services (CMS).
The volatility in Washington, D.C. could mean the shutdown lasts days to weeks, and TMA will share additional information via Texas Medicine Today as the situation develops. Here is what physicians need to know so far:
Medicare/Medicaid: The CMS contingency plan states that during a lapse in funding, the Medicare program will continue. CMS also says it has sufficient funding for Medicaid to fund the first quarter of 2026 and is maintaining the staff necessary to make payments to eligible states for the Children’s Health Insurance Program.
Medicare Administrative Contractors (MACs) have been instructed to implement a temporary claims hold of 10 business days, which AMA says should have minimal impact on physicians due to the 14-day payment floor. “The hold prevents the need for reprocessing large volumes of claims should Congress act after the statutory expiration date,” states a CMS Medicare Learning Network Connects special edition email newsletter that, as of this writing, had not yet been publicly posted. Physicians may continue to submit claims during this period, but payment will not be released until the hold is lifted. For the latest information, AMA recommends physicians monitor their MAC’s website (Novitas in Texas) and this CMS webpage.
“In the past, Congress generally has restored lapsed policies back to the effective date of the shutdown. During the shutdown, the AMA is monitoring any potential delays in Medicare claims processing or other Medicare payment problems that could result from federal staffing reductions at CMS, including during the shutdown,” said AMA CEO and Executive Vice President John Whyte, MD, MPH.
Telehealth: Physicians who provide telehealth services to fee-for-service Medicare patients should be aware that the Medicare telehealth flexibilities lapsed on Sept. 30 for most care and congressional action is required to restore that waiver. The exceptions are patients being treated for mental health and/or behavioral health disorder (including substance use disorders), stroke, and monthly end-stage renal disease visits for home dialysis. Otherwise, telehealth services are limited to rural areas as they were before the COVID public health emergency, and patients cannot receive telehealth services in their homes. The ability to provide audio-only services to Medicare patients also lapsed, as did the Acute Hospital Care at Home program.
The CMS newsletter suggests “practitioners who choose to perform telehealth services that are not payable by Medicare on or after Oct. 1, 2025, may want to evaluate providing beneficiaries with an Advance Beneficiary Notice of Noncoverage.”
However, AMA notes physicians in certain Medicare Shared Savings Program accountable care organizations can continue to provide and be paid for telehealth services.
Other services: CMS says it is continuing federal insurance marketplace activities, such as eligibility verification. Other nondiscretionary activities including health care fraud and abuse control and Center for Medicare & Medicaid Innovation activities are also continuing.
However, AMA reports that funding extensions for community health centers, the National Health Service Corps, and teaching health centers that operate graduate medical education programs expired on Sept. 30, and the 1.0 work geographic practice cost index floor extension expired on Oct. 1. Additional programs that have lapsed include: special diabetes programs; public health emergency authorities (e.g., Public Health Emergency Fund); increased inpatient hospital payment adjustment for certain low-volume hospitals; the Medicare-Dependent Hospital program; quality measure endorsement, input, and selection; and outreach and assistance for low-income programs (e.g., area agencies on aging).
TMA wants to hear from you. If you or your practice staff experience Medicare payment delays, telehealth obstacles, or other concerns, please let us know through TMA’s Knowledge Center to help inform advocacy.
Amy Lynn Sorrel
Associate Vice President, Editorial Strategy & Programming
Division of Communications and Marketing
CMS Releases 2024 MIPS Scores

The Centers for Medicare & Medicaid Services (CMS) has released MIPS performance feedback and final scores for the 2024 performance year. Sign in to the Quality Payment Program (QPP) website using your Health Care Quality Information Systems (HCQIS) Access Roles and Profile (HARP) system credentials to view your feedback from CMS. The targeted review period will be open for approximately 60 days, beginning with the release of final scores and closing 30 days after the release of MIPS payment adjustments that CMS plans to announce in one month.
VA Seeking Refunds for Past CHAMPVA Claims
The U.S. Department of Veterans Affairs (VA) announced it aims to recover more than $41 million in “overpaid claims” paid to physicians and other health care professionals and entities through the Civilian Health and Medical Program of the Department of Veterans Affairs (CHAMPVA) program.
Texas Medical Association staff caution that physicians receiving CHAMPVA refund requests should take several steps to satisfy the VA request without immediately losing payment for care already delivered:
- Confirm the legitimacy of the request letter. As refund letters typically come from third-party companies, a practice may call CHAMPVA and ask them if the third-party company is one they contracted with to collect the overpayment;
- Check the letter for details on how to appeal, including any payment or appeal deadlines; and
- Check the letter for information about which insurer VA says is responsible for payment.
From there, physicians can choose one of two actions. If it appears the alleged overpayment has been identified in error, start the appeal process to try to keep the CHAMPVA payment already received. If not pursuing an appeal – or if an appeal is ultimately denied – refund the overpayment to VA and seek payment from the insurer VA says is responsible for payment. For a physician seeking payment from that insurer, TMA recommends including, as part of that request, the initial CHAMPVA explanation of benefits and any information from VA indicating that the insurer is the proper payer, especially if the filing deadline has passed.
For assistance with CHAMPVA refund requests or other payment matters, contact TMA’s Physician Payment Resource Center.
Separate Services, Same Date of Service
With health plans increasingly adopting payment protocols that hinder physicians from providing multiple services on the same day – despite previously covering such services – delegates adopted policy calling on TMA to “advocate for legislation or regulation that would prevent Medicaid and commercial payers from denying payment for distinct, separate services provided on the same day.”
Delegates agreed with physicians’ concerns that these payer practices often force patients to forego care.
“This especially hurts patients who either have to travel long distances to see their physician or have transportation issues that prevent them from making multiple trips,” Odessa allergist and immunologist Vivek Rao, MD, wrote in online testimony on behalf of the Lone Star Caucus
Other measures adopted by the house to eliminate payment-related barriers to patient care direct TMA to pursue state-level legislation or regulation that:
- Prohibits insurers, plan sponsors, third party administrators, and other contracted identities from recouping previously paid claims due to retroactive termination of patient coverage;
- Imposes payer communication standards – with penalties – that provide patients, physicians, and others with timely access to a live representative; and
- Expedites prior authorization approvals for hospice care in emergency and acute care settings, eliminates deductibles for hospice care, and provides clear disclosures detailing hospice care benefits in policy documents as well as online.
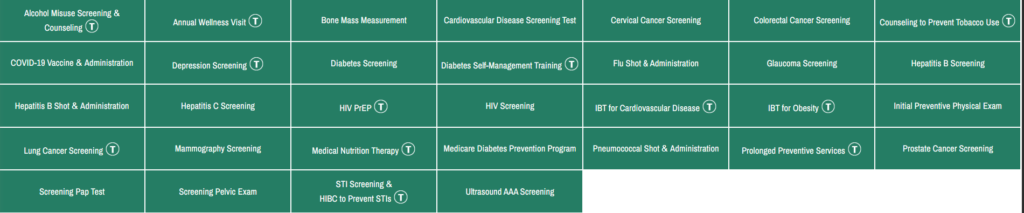
Medicare Preventive Services – Revised
The above link will lead you to MLN Educational Tool, where you can click a service and see the changes.
HS Connect Issues

You may have been experiencing issues with HS Connect. One office reported to POET (thank you) they had been in contact with HS Connect. And was told that on January 1, 2025 HS Connect had a major update. You may already guessed, it failed (Majorly in Texas). Our source was told that HS Connect is having to enter Texas Data by hand. What you are seeing when you pull up the screen is 2024 data.
For more information call: HS Connect Help Desk (866) 952-7596 , option 2 or email [email protected]
Modifier 25 Fact Sheet from Novitas
Modifier 25 Fact Sheet
Modifier 25 is defined as a significant, separately identifiable evaluation and management (E/M) service by the same physician or other qualified health care professional on the same day of a procedure or other service.
Physicians of the same specialty in the same group practice are considered the same physician; therefore, they must bill and be paid as though they were a single physician.
Appropriate Use
Use modifier 25 with the appropriate level of E/M service.
- Modifier 25 indicates on the day of a procedure, the patient’s condition required a significant, separately identifiable E/M service, above and beyond the usual pre- and post-operative care associated with the procedure or service performed.
- E/M service may occur on the same day as a procedure. Medicare allows payment when the documentation supports modifier 25.
- A minor surgical procedure performed has a global period of 0-day or 10-day listed on the Medicare physician fee schedule (JH) (JL) and meets the definition of modifier 25.
Global Surgery
Global surgery is defined as all necessary services normally furnished by a surgeon before, during, and after a procedure. Medicare payment for a surgical procedure includes pre-operative, intra-operative, and post-operative services routinely performed by the surgeon or by members of the same group with the same specialty.
Do not use modifier 25 when billing for services performed during a post-operative period if related to the previous surgery. Related follow-up examinations by the same provider during the global period of a previous procedure are included in that procedure’s global surgical package.
- For an unrelated E/M service during the global period of a previous procedure, you may be able to report an appropriate E/M code with modifier 24 (unrelated evaluation and management service by the same physician during a postoperative period) appended.
- The E/M is for a new problem not related to the patient’s previous complaint or procedure.
- Append modifier 57 (decision for surgery), rather than modifier 25, if the E/M service prompts the decision to render a major procedure within 24 hours of the E/M service. Major procedure is defined as one with a 90-day global period.
National Correct Coding Initiative (NCCI) Procedure-to-procedure (PTP) edits
The NCCI promotes national correct coding methodologies and controls improper coding leading to inappropriate payment. The PTP code pair edits are automated prepayment edits preventing improper payment when reporting certain codes together for Part B-covered services on the same day by the same physician.
When both correct coding and global surgery edits apply to the same claim by the same physician, we’ll first apply the correct coding edits. Then, we’ll apply the global surgery edits to the correctly coded services
References:
E/M visit complexity add-on HCPS code G2211,
Effective for dates of service on and after January 1, 2025:
HCPCS code G2211 is payable when an associated office and outpatient (O/O) E/M base code (CPT codes 99202-99205 or 99211-99215) is reported with modifier 25 for the same patient by the same provider and a Part B preventive service, immunization administration, or annual wellness visit service identified in attachment 1 in Change Request (CR) 13705 is also present for the same date of service.
For claims not containing one of the identified services above or dates or service prior to January 1, 2025:
- Claims will deny when HCPCS code G2211 and an associated office and outpatient (O/O) E/M visit (CPT codes 99202-99205 or 99211-99215) is reported with modifier 25 for the same patient by the same provider on the same date of service:
- Separately identifiable visits occurring on the same day as minor procedures (such as 0 or 10-day global procedures) have resources sufficiently distinct from costs associated with furnishing stand-alone O/O E/M visits to justify different payment.
References:
- Change Request 13705 – Allow Payment for Healthcare Common Procedure Coding System (HCPCS) Code G2211 when Certain Part B Preventive Services are Provided on the Same Day
- MLN Matters article MM13473 – How to Use the Office & Outpatient Evaluation and Management Visit Complexity Add-on-Code G2211
- MLN Matters article MM13272 – Edits to Prevent Payment of G2211 with Office/Outpatient Evaluation and Management Visit and Modifier 25c
Inappropriate use
Avoid denials of claims with an appropriate use of modifier 25
- Do not report HCPCS code G2211 when modifier 25 is reported on an associated E/M visit (CPT codes 99202-99205 and 99211-99215) for claims not containing a Part B preventive service, immunization administration, or annual wellness visit service or dates of service prior to January 1, 2025.
- Do not use modifier 25 on HCPCS code G2211.
- Do not use modifier 25 on CPT code 99211
- Do not use modifier 25 by a physician other than the physician performing the procedure or physician of the same specialty in the same group practice.
- Do not use modifier 25 when documentation does not support a significant, separately identifiable E/M service.
References:
- CMS IOM Pub. 100-04 Medicare Claims Processing Manual, Chapter 12, section 40.2-40.5
- CMS IOM Pub. 100-04 Medicare Claims Processing Manual, Chapter 23, section 30.2
- E/M Service-specific coding instructions
- Frequently Asked Questions: Evaluation and management services
- Global Surgery Fact Sheet
- Global surgery & related services
- Global surgery calculator (JH) (JL)
- Local contractor pricing references
- MLN Matters article MM13452 – Medicare Physician Fee Schedule Final Rule Summary: CY 2024
- Modifier 25 tip sheet

Telehealth Breaking News

The below information was received today 12/26/2024, from Betsy Nicoletti
Medicare practitioners and patients can continue to perform/receive telehealth services as they have since the start of the pandemic for the next three months.
The first keep-the-government-open bill from Dec. 20 extended Medicare telehealth for two years. It didn’t pass. The bill that passed and was signed into law extends telehealth for Medicare patients as we know it now until March 31, 2025. Then, Congress must ACT again or we have the return to the pre-pandemic rules
Does this mean we can use the new CPT telehealth codes 98000-98015?
NOT FOR MEDICARE PATIENTS
98000-98015 have a status indicator of INVALID
Continue to use office visit codes with POS 02 or POS 10
And Other Payers?
Sadly, each payer can make their own telehealth rules.
TMA Webinar Helps Equip Physicians for 2025
Medicare Fee Schedule
With the Centers for Medicare & Medicaid Services’ (CMS’) 2025 Medicare Physician Fee Schedule set to take effect Jan. 1, the Texas Medical Association is preparing physicians for changes in payment and coding, telemedicine, and quality and value-based care arrangements, among other areas.
Recent Comments